Human Factors-Designed Triple Test for HIV, HBV, and HCV Infection in Whole Blood Using Target Amplification, Signal Amplification, and Crumpled Graphene Biosensor Readout
NIH Project Number: 1R01AI194914
Access to frequent, accurate, and highly sensitive HIV viral load monitoring is a critical component of early infection diagnosis, HIV antiretroviral therapy, and routine diagnostic testing to keep people informed and help them maintain their HIV viral load status. The prevalence of co-infection with other viruses that present with similar symptoms, such as Hepatitis B virus (HBV) and Hepatitis C virus (HCV), drives the clinical need for multiplexed testing from the same blood sample. Although extensive research and product development has been applied to point-of-care (POC) viral load testing, the current paradigm of nucleic acid tests and antigen assays is inherently complex, lacks robustness, and is costly, which prohibits adoption in settings that serve key populations seeking care in lower stigma locations (e.g., community health centers vs. hospital settings).
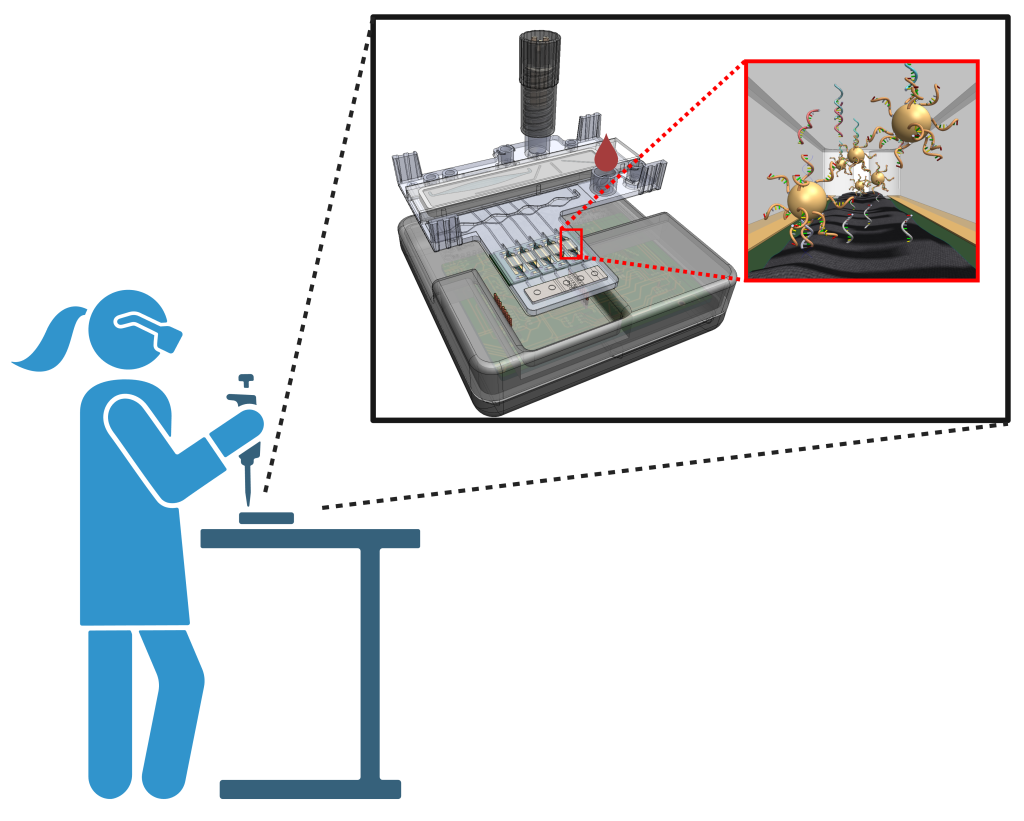
We seek to address this societal need, and technological gap, by advancing testing methods through the development of a microfluidic cartridge, molecular biology method, biosensor, and detection instrument that will simultaneously detect HIV, HBV, and HCV viral loads. This POC test will require minimal whole blood volume (100 mL), take <30 minutes for sample-to-answer, and have superior sensitivity to PCR. Our nucleic acid test performs sample pre-processing in a microfluidic cartridge followed by virus-specific activation of CRISPR/Cas enzyme that rapidly releases large numbers of gold nanoparticle reporters that are subsequently captured and detected on crumpled graphene impedance-based biosensors. Our handheld, inexpensive (<$50) POC platform communicates its measurements to a mobile device (smartphone or tablet) to process current/voltage measurements from a custom circuit board. The affordable estimated cost per test (~$5) is based on our experience using the Additive Manufacturing approach for cartridge fabrication, combined with the low microfabrication cost of resistive sensors on silicon.
Our preliminary data demonstrate the effectiveness of nucleic acid extraction from whole blood, the sensitivity/selectivity of the assay approach, and the sensitivity of the biosensors. The system will be evaluated using a rigorous tiered approach by spiking target nucleic acid sequences and viruses into buffer and whole blood for initial characterization of detection limits. We will validate the POC platform’s ability to detect HIV, HBV, and HCV in whole blood using clinical samples provided by our hospital collaborators in Illinois. Throughout the development and testing of the POC test, we will conduct rigorous human factor engineering and acceptability research with our behavioral scientist collaborators, who will mediate this iterative process to reflect the needs of clinicians, scientists, healthcare workers, health technicians, and potential end users represented by a scientific advisory group. The resulting platform will make a significant impact upon public health to those who lack easy access to sensitive, inexpensive, and triple rapid viral testing outside of traditional clinical settings.
Point-of-Care Microfluidic Biochip for Biomarkers Monitoring for Contributing in Early Sepsis Diagnosis
NIH Project Number: 1R01AI148385
Sepsis, a life-threatening organ dysfunction caused by a dysregulated host response to infection (Sepsis- 3 definition), is the leading cause of death and most expensive condition in hospitals. Annually, > 30 million people affected worldwide, with at least 1.7 million adults developing sepsis (nearly 270K die) at a cost of $24 billion per year in the U.S. Patients diagnosed with sepsis and no ongoing sign of organ failure have about a 15-30% chance of death. However, the mortality rate can increase up to 40-60% for severe sepsis or septic shock patients. One in three patients who die in a hospital have sepsis. One major factor in these rising mortality rates is the inability to accurately and quickly diagnose potentially septic patients. Likewise, sepsis is a leading cause of hospital readmission (higher proportion than hospitalizations for heart attack, heart failure, COPD, and pneumonia in the U.S.). EDs and ICUs rely on monitoring extremely non-specific parameters (e.g. fever, low blood pressure, increased heart rate) to initiate a clinical diagnosis and begin treatment. These crude indicators cause doctors to mistake early stage sepsis with several other diseases. A positive diagnose of early onset sepsis is critical because mortality increases with delays in treatment. Survival rates have been reported to drop by 7.6% every hour that the proper antibiotics are not administered, and these delays compound unnecessary hospital costs.
Over the last 30 years, clinics have used different criteria such as SIRS, LODS and SOFA or qSOFA as screening tools to assess the severity of organ dysfunction in a potentially septic patient. Common factors among these criteria are non-specificity and very high false positive rates. For patients with positive criteria, the final diagnostic test is a blood culture that may take up to 5 day for a negative result. Likewise, blood culture has a very high false negative rate (> 60%) and does not work for fastidious pathogens such as Chlamydia pneumoniae. More importantly, blood culture cannot be a gold standard method for sepsis diagnosis. This technique only detects the presence of bacteria in the bloodstream (bacteremia), which does not necessarily indicate illness. Many non-bacteremic infections can also cause life-threatening sepsis. In order to improve the accuracy and sensitivity of sepsis diagnosis, the Sepsis-3 definition underscores the requirements for both pathogen detection and information about the personalized state of the immune system of the patient. Therefore, we propose to focus our efforts on monitoring selective biomarkers of this immune response. However, no single, or even a combination of biomarkers has been validated for the diagnosis of sepsis. Because no single biomarker is specific enough to predict sepsis, we propose to develop a point-of-care microfluidic biochip for measuring cell-surface and plasma-proteins biomarkers that will be used for contributing in early sepsis diagnosis. The microfluidic biochip will provide a complete white blood cell count (WBC), as well as quantification of CD64 expression on neutrophil (nCD64), procalcitonin (PCT), C-Reactive Protein (CRP) and Interleukin 6 (IL-6). Multiple studies have demonstrated the high sensitivity of these biomarkers to sepsis. The proposed device will combine for the first time the analysis of cell-surface proteins and plasma proteins biomarkers from the same sample of blood. Such a device, combined with the routinely test performed in the hospitals, could significantly accelerate the diagnosis of sepsis and as consequence the clinical decision, to provide the correct treatment to the patients.